Healthcare
Plasma Donation Center Queue Management: Calm New vs Returning Donor Lobbies
How plasma and blood-donation desks run fair walk-in Ticket lines—new donor vs returning vs screening vs eligibility Services, Counters, QR join, and an honest split from donor OS tools.
· Esperaly Editorial · 10 min read
Saturday morning at a plasma centre rarely fails because a phlebotomist cannot start a donation. It fails because new-donor paperwork, returning donors who already know the path, screening callbacks, and short “am I deferred?” questions share one informal lobby crowd. Someone waiting five minutes for a staff answer stands behind a first-time registration that still needs vitals and history. Floor leads shout first names across snack tables while a chair sits empty for the wrong Ticket type. That is the job plasma donation queue management is supposed to solve—not a donor-management system rewrite, not an EMR, and not a fake #1 ranking for healthcare software.
This guide is for commercial plasma centres, community blood-donation desks with a real walk-in share, and multi-site operators that run same-day donor lobbies alongside booked slots. You will get a Ticket, Counter, and Service model that matches how donors already talk, a practical floor setup on devices you already own, and an honest split from donor OS, eligibility tools, and chair-scheduling suites. For industry context, see Esperaly for healthcare. Patient blood-draw lobbies (not donor floors) belong on diagnostic lab queue management—similar fairness problem, different Service map. Same-day sick-visit clinics live on walk-in clinic queue management.
What plasma donation queue management actually does
Strip the category to the loop that matters when the lobby is standing room only and two job lengths share one rope at reception:
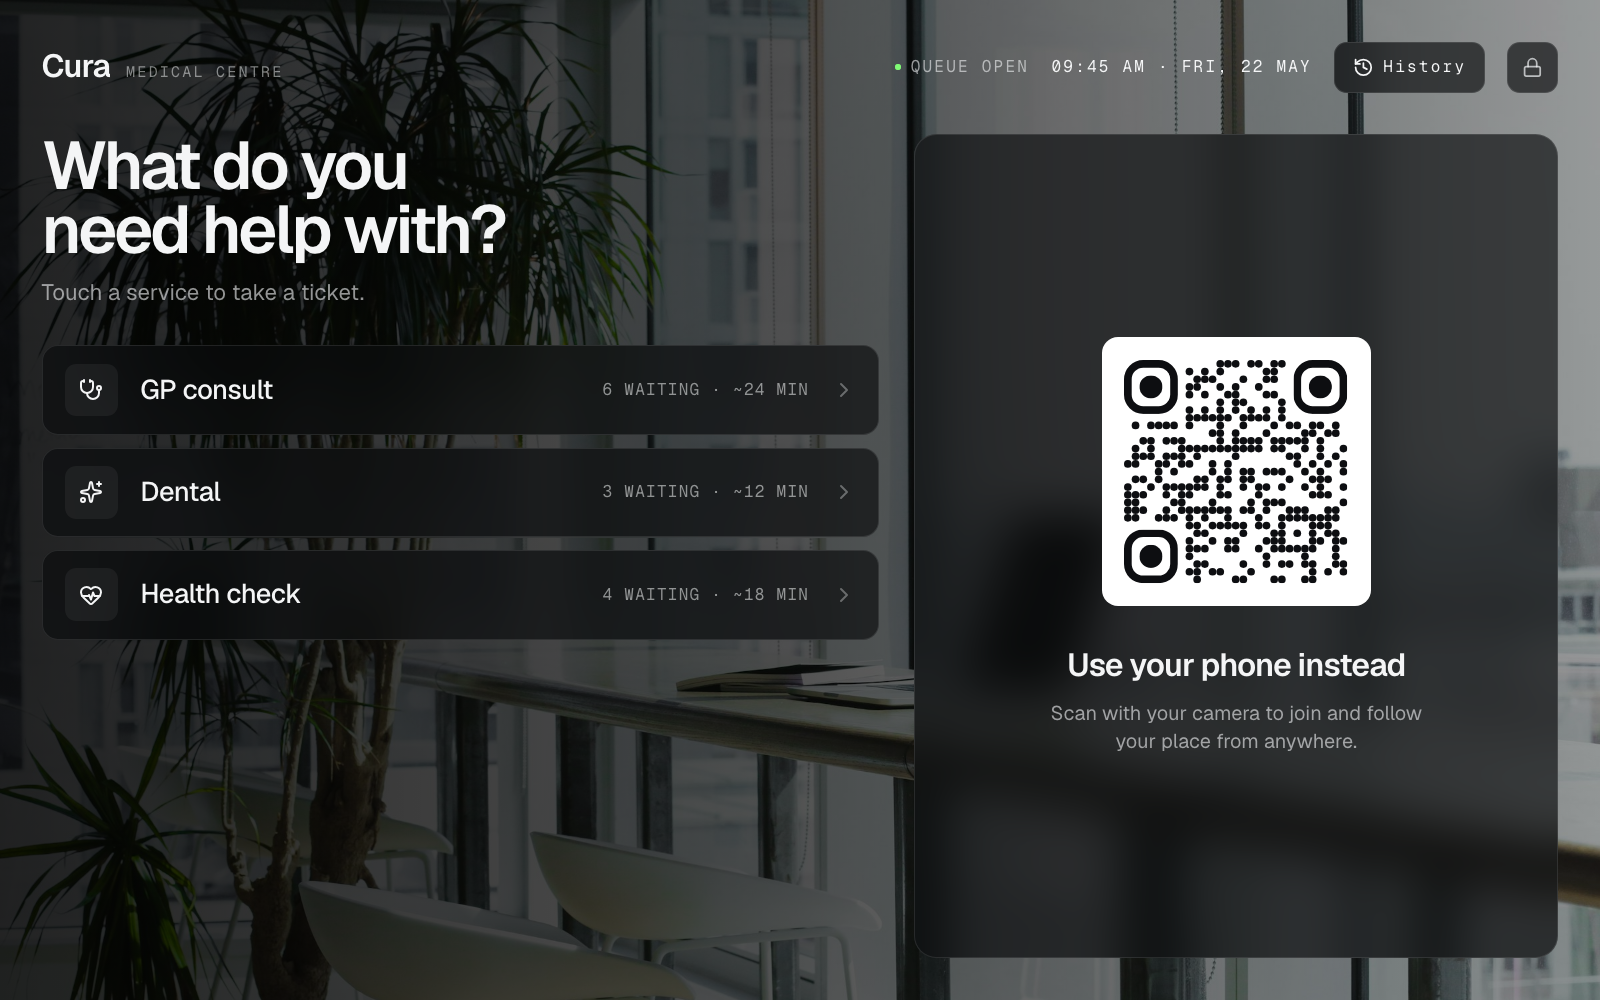
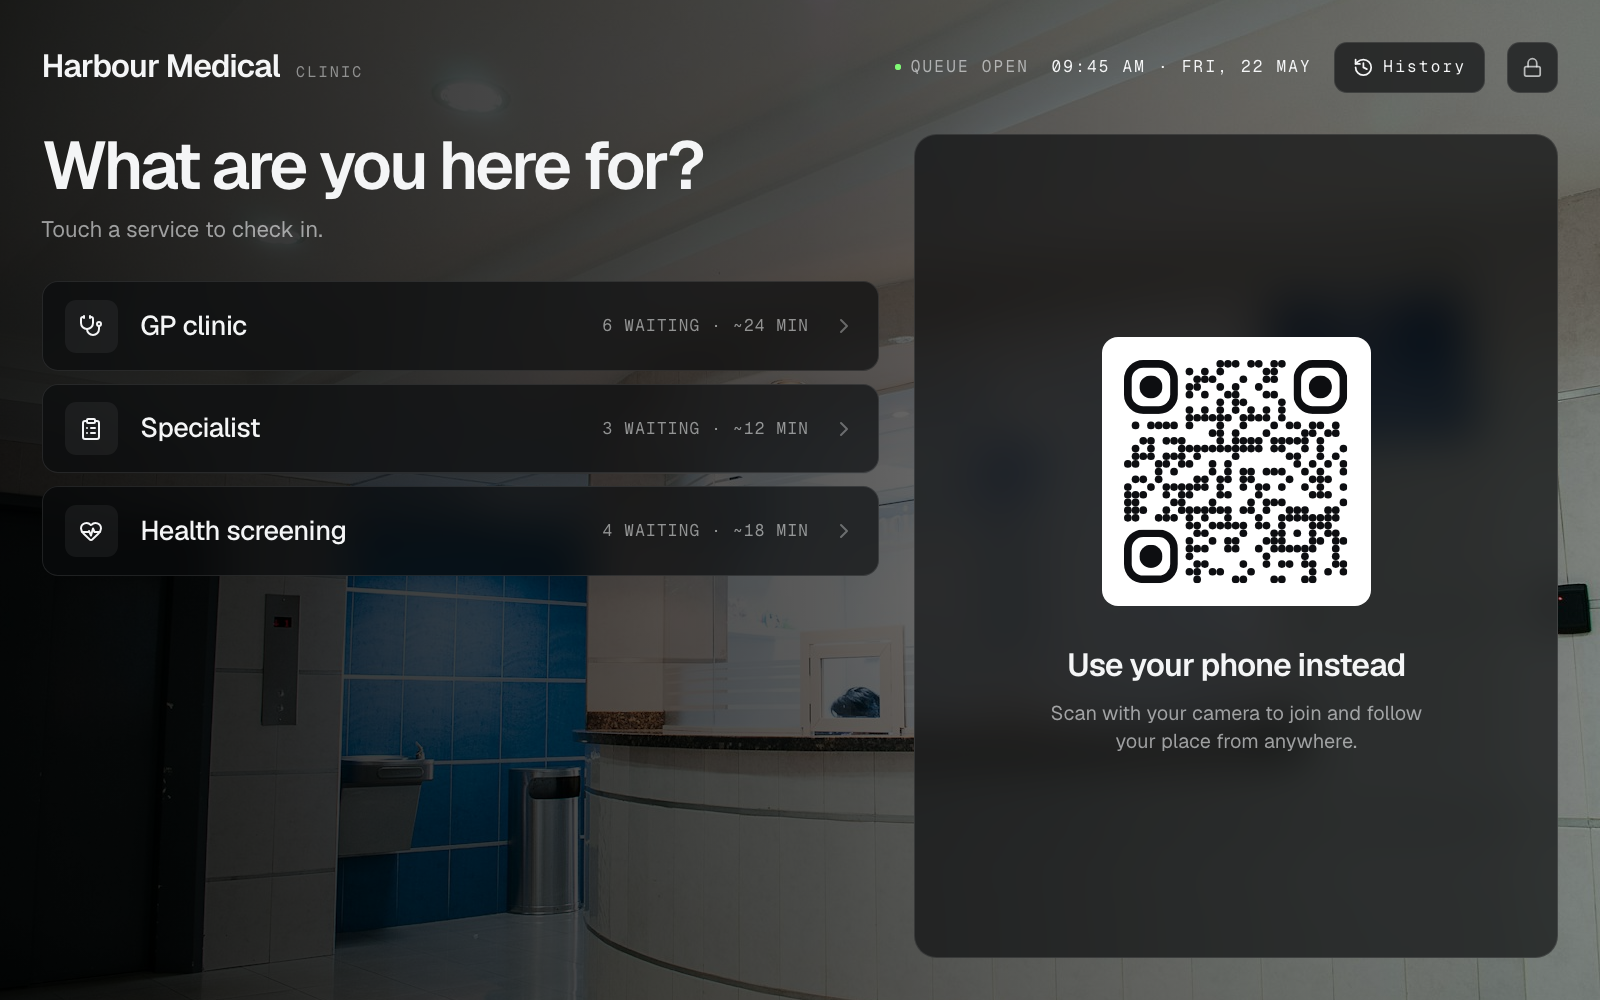
- A donor joins with a Ticket (phone QR after they clear the door policy, or a tablet at the welcome desk)
- They choose a Service that matches real need—new donor / first visit, returning donation, screening / vitals recall, deferred / eligibility question, or admin / payment / enquiry—not an internal SOP code
- Staff call the next Ticket at a Counter (a registration window, a screening bay that can take the next person, or a floor lead who opens a second desk for the rush)
- The lobby stays informed—on the phone Ticket and, optionally, a now-serving board near the seats (labels that respect privacy policy)
If a vendor cannot show that loop without a sales deck about full donor OS migrations, plasma-device integrations, or a scheduling suite you did not ask for, you are shopping for a different category. The free plan is the fastest way to see join → wait → call on everyday devices.
Why one clipboard line fails on the donor floor
Paper lists and “who got here first?” memory work until a short eligibility question lands behind a forty-minute first-time path, two returning donors share one sofa bank with no shared view of who is next, or a side whisper becomes the real queue. Donors absorb it as favouritism and a crowded, anxious lobby—especially when someone is fasting, tired, or already deferred once this month. Screeners absorb it as constant status questions while they try to keep chairs filled. Floor leads absorb it as empty beds while the wrong Service waits at the front of a single shouted list.
Digital Tickets make order visible. Donors see place in line for the Service they chose. Staff see who is next for each Counter without guessing across registration, screening, and the donation floor. When someone challenges fairness at the desk, you have a sequence to point at instead of memory. That alone often pays for the tool on a single peak Saturday.
For the broader trade-off between phone-based waits and classic walk-in tickets, read virtual queue vs walk-in ticket queue. Donor centres usually want both: people free to wait in the car or outside when policy allows (calmer lobbies, fewer capacity headaches), plus a clear call when a Counter opens—without turning the parking lot into an unmanaged free-for-all.
Map the floor with Services and Counters
Plasma queue projects fail when teams invent eighteen Services nobody will tap, or when they collapse every ask into “donate.” Start with the jobs that actually change wait length or which staff member can help.
Services that match how donors actually ask
- New donor / first visit — the long path: paperwork, screening, and first donation; should not poison a single rope with returning Traffic when volume is high
- Returning donation — the volume driver on many floors; shorter when history and eligibility are already known
- Screening / vitals recall — called back for a second look or incomplete vitals; keep the name donor-facing and honest
- Deferred / eligibility question — brief asks that should not steal every open Counter from full donation paths
- Admin / payment / enquiry — stipend questions, card updates, and short desk asks that are not a donation start
Keep names donor-facing. People will not tap “PLASMA-OPS-03.” If you only have one open desk, you can still use Services for reporting and fairness even when every Ticket is called from one Counter. Blood-donation drives that run a thinner Service map (walk-in vs booked arrival) still benefit from the same Ticket loop—just do not pretend a mobile drive is a full commercial plasma OS.
Counters that match how you staff the floor
- One Counter per open registration or screening bay when each associate runs their own Call Next for the Services they cover
- A shared “next available” Counter when anyone free takes the next Ticket of a given Service
- A short eligibility or admin Counter when those asks should not block full new-donor or returning paths
Capacity planning for desks is the same maths as any walk-in line—see how many Counters do you need and sanity-check wait assumptions with the wait time estimator. Splitting Services too early creates empty lanes; waiting too long creates the classic “returning donor stuck behind first-time paperwork” complaint. The companion guide on when to split queue Services helps you decide. Multi-desk handoff patterns are covered on multi-counter.
Note the boundary with the donation floor itself. Chair assignment, recovery observation, and device workflows stay in your donor OS. The queue answers “who is next at this Counter?” so screening and registration stay fair—not “which bed is free” as a clinical inventory system.
Floor setup without proprietary lobby hardware
You do not need a manufacturer kiosk tower to calm a donor lobby. Most centres already have a tablet, a spare laptop, and phones donors bring themselves—after your door and ID policy lets them in.
- Join — print a QR for QR join just past the welcome desk (or at a tablet for visitors who prefer not to use their phone). Place the code where joining does not create a second unmanaged line at the door.
- Call — Counter view on the desk laptop or a tablet at the screening bay; Call Next when a Counter is free
- Inform — phone Ticket status for donors waiting outside or in the car when policy allows; optional browser waiting-room display if the lobby needs a shared board (see also queue display board software)
Browser-based tools beat “buy our pedestal” pitches for most single centres and small multi-bay floors. If someone insists you cannot run a fair line without specialized ticket printers, read do you need expensive queue hardware. Hardware-heavy customer-flow suites can be the right buy for a large multi-branch programme; a single centre usually needs Service-tagged Tickets and Call Next first—see Qmatic alternative for walk-in desks and Wavetec alternative for walk-in desks when that evaluation is on the table.
Keep donor OS, eligibility, and chairs in their lane
Plasma donation queue software organises who is next. It does not replace your donor management system, eligibility / deferral tools, plasma device software, stipend payments, or clinical documentation. Donors still get screened, collected, and recorded in the systems your quality and compliance teams already expect; the Ticket only answers “whose turn is it at this Counter?”
That boundary matters when vendors blur categories. Donor-floor products often pitch SMS, virtual rooms, chair inventory, and eligibility data capture in the same breath as the line. Capture what compliance requires in the tools built for that job. Keep the public Ticket lean—see QR Ticket privacy basics—and never treat the now-serving board as a place to display donor IDs, medical details, or phone numbers meant for staff only.
Esperaly is Ticket / Counter / Service flow—not a donor OS, not an EMR, not a plasmapheresis device console, and not an appointments engine. Keep booking tools for reserved donation slots that truly need a calendar. Use the queue for the walk-in lobby so returning donors and short eligibility asks are not one shouted name list.
If you are evaluating Waitwhile-, Qminder-, or Qwaiting-shaped tools for a larger programme, start with Esperaly vs Waitwhile, Esperaly vs Qminder, and Esperaly vs Qwaiting—then keep the local counter on a Ticket / Counter model you can staff this week. Pharmacy windows and clinic desks that sit near a donor site are covered in pharmacy queue management and queue software for small clinics—related fairness problems, different Service maps.
A practical week-one rollout
Ship a thin loop before you decorate the vestibule with six QR stands:
- Morning — name four Services (new donor, returning donation, screening recall, deferred / eligibility or admin) and open Counters for the bays you will staff today
- Afternoon — print one QR past the welcome desk; put Counter view on the desk laptop; brief screeners on Call Next and “no shadow clipboard”
- Quiet hour — staff join test Tickets, call them, confirm any board matches
- First peak day — run live with one lead watching for whispered side lines; kill the paper list the same day
- End of week — review abandonments, average wait by Service, and whether donors misunderstood Service names
For a generic launch checklist, reuse set up a digital queue in under an hour. Centre-specific work is mostly naming new vs returning vs eligibility Services and deciding where join sits relative to ID check. Train staff on the call habit with staff training: call next Ticket. If walkaways after join are your pain, pair the rollout with reducing walk-in queue no-shows.
What to evaluate before you buy
Score vendors yourself. Useful questions for centre managers and floor leads:
- Can a verified adult join in under a minute without installing an app—after your door policy, not instead of it?
- Can staff answer “who’s next for returning donation?” on one screen while new-donor and eligibility Tickets stay visible?
- Does pricing follow desks/Counters, or per-user seat taxes you will resent by month two?
- Can you go live this week on devices you already own?
- Does the vendor pressure you into proprietary kiosks, a donor OS rewrite, or a full chair-inventory suite before the lobby queue works?
- Are they honest that eligibility, collection, and payments stay in your existing licensed tools if those already work?
Run the monthly cost against your Counter count with the queue cost calculator. Skip vanity feature theatre—the companion post what to ignore when buying queue software still applies behind a donor rope. For a wider SMB shortlist shaped around walk-in desks (not another “best of” clone of this article), see the best queue management software for small business guide. Pricing context lives on queue management system price and Esperaly pricing.
When to wait before buying
Queue software is the wrong first project if:
- Centre Wi‑Fi cannot keep a phone or tablet online at the desk
- Leadership has not decided how new donors and short eligibility asks interleave with returning donations
- The real pain is a broken donor OS, deferred-donor workflow, or chair inventory process—not the crowd after the door
- Nobody will own Call Next habits for the first Saturday peak
Fix those first. A clean Ticket system with no owner becomes optional decoration by the next mobile drive weekend.
Get a calmer plasma donation queue this week
Plasma donation queue management earns its keep when donors know their place, screeners stay on the Counter that matches the ask, and the lobby stops mediating memory—while eligibility and collection stay in the tools built for them. Start with clear donor-facing Services, honest Counter capacity, and a QR arrivals can scan without a lecture.
When you are ready to test with your real Service names, start a 14-day trial or explore healthcare positioning. Prove join → wait → call on one quiet midweek afternoon. If that loop feels obvious to your floor team, you have the right class of tool.